Call Us +65 6884 6788

July 2026

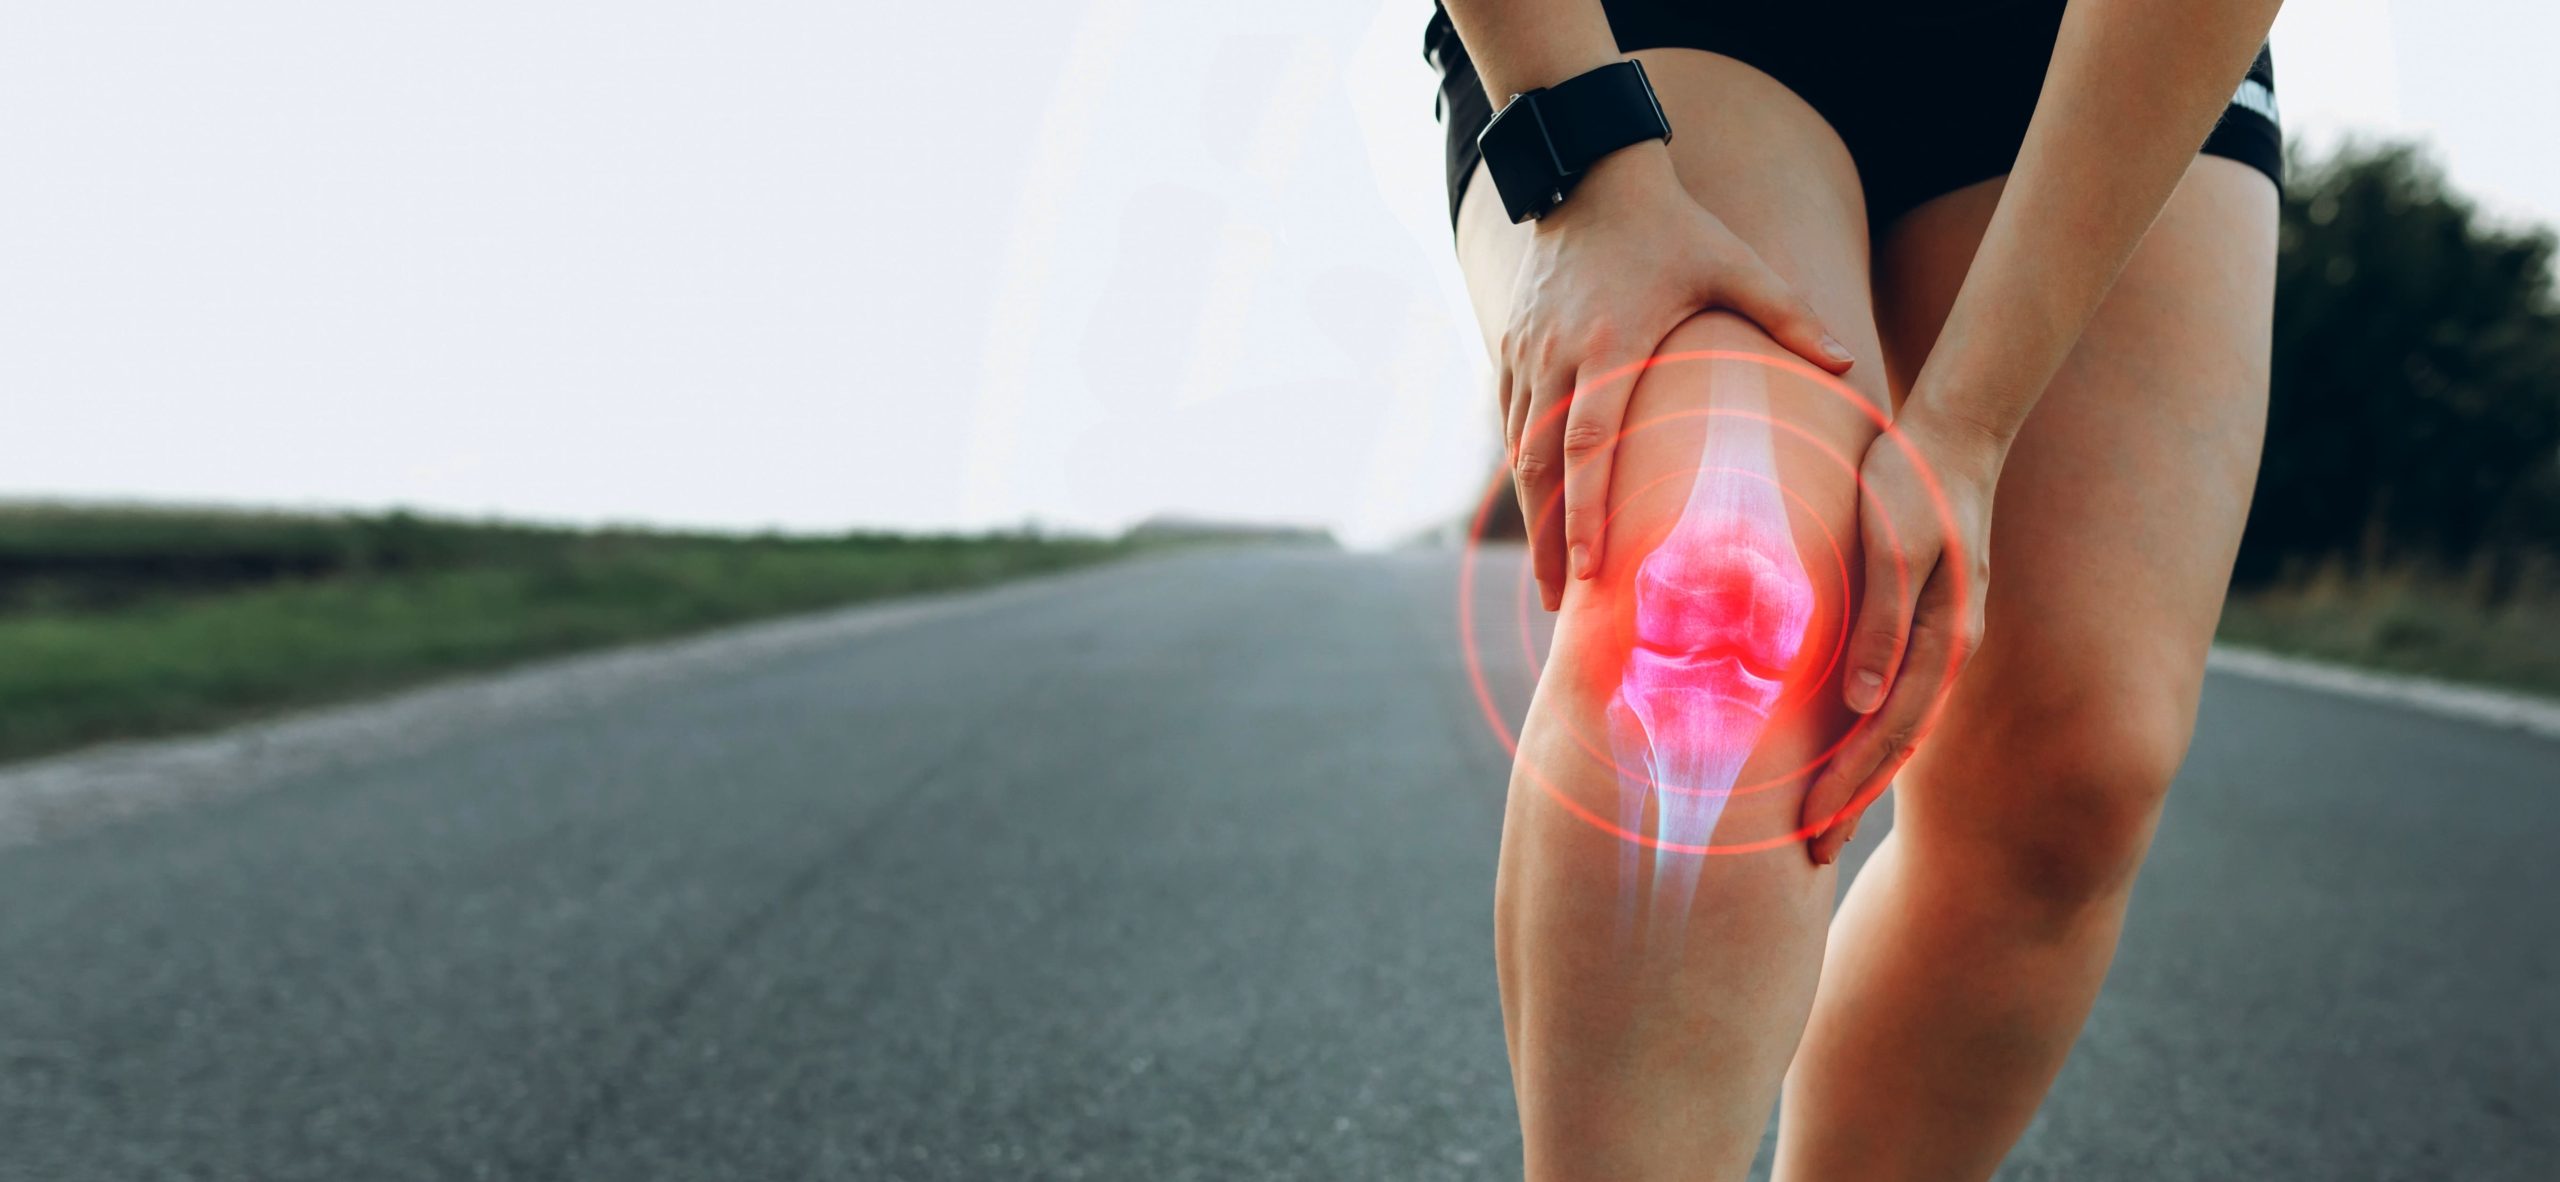
Knee pain after a fall, a sudden twist during sport, or even just a misstep on the stairs can leave you wondering whether something is seriously wrong. Understanding meniscus tear symptoms can help you make a more informed decision about your next step.

What Is a Meniscus Tear?

A meniscus tear is a rupture of the cartilage pads inside the knee joint that cushion and stabilise the joint during movement. Each knee contains two C-shaped pieces of cartilage, one on the inner side (medial meniscus) and one on the outer side (lateral meniscus). Together, they act as shock absorbers between the thigh bone and shin bone, distribute your body weight evenly across the joint, and help keep the knee stable during everyday activities.

Think of the menisci as the rubber washers inside a tap fitting. They prevent metal-on-metal contact and keep everything moving smoothly. When one tears, the mechanics of the knee change, and you may begin to notice pain, stiffness, or unusual sensations during movement.

Tears can range from small, partial fraying to complete ruptures that affect the entire thickness of the cartilage. The size, depth, and location of the tear all influence how symptoms present and which treatment approach may be appropriate.

How Traumatic and Degenerative Tears Differ

Meniscus tears generally fall into two categories.

Traumatic tears occur suddenly, typically during sport or physical activity. A sharp pivot, a deep squat under load, or a direct impact to the knee can cause the cartilage to tear in an instant. These injuries are common in football, basketball, and other sports that involve rapid changes of direction. You may recall the exact moment it happened, often accompanied by a popping sensation and immediate pain.

Degenerative tears develop gradually over time as the cartilage weakens with age. The meniscus becomes less resilient and more prone to tearing from relatively minor movements, such as rising from a low chair or stepping off a kerb. There may be no single identifiable incident.

Both types can produce similar symptoms, including pain, swelling, and reduced range of motion, but may follow different treatment paths.

Key Meniscus Tear Symptoms

Not every meniscus tear announces itself dramatically. Some tears cause intense, immediate pain, while others produce only a dull ache that builds over days.

Pain Along the Knee Joint Line

One of the most telling signs of a meniscus tear is pain felt along the inner or outer edge of the knee, where the joint line sits. This is the crease you can feel when you bend your knee slightly and press along either side.

The pain may be sharp during activity and duller at rest. You might notice it when squatting down, such as when sitting on a low stool at a hawker centre, or when kneeling to pick something up. In some cases, the pain is only present during specific movements rather than constantly, which can lead people to underestimate the injury.

Swelling That Develops Gradually

Unlike the rapid swelling that follows an ACL injury, meniscus tear swelling often builds slowly over 24 to 48 hours after the initial injury. The knee may feel puffy or tight, and you might notice it looks slightly larger than the uninjured side.

This swelling occurs because the torn cartilage triggers an inflammatory response inside the joint. Persistent puffiness that does not settle with rest warrants attention.

Locking or Catching Sensation

A torn fragment of meniscus can sometimes fold or shift into a position that interferes with normal knee movement. This produces a locking sensation, where the knee becomes stuck and cannot straighten fully, or a catching feeling, a brief snag or click during movement.

True locking (where the knee cannot be fully extended) is a more significant sign and generally warrants prompt evaluation.

Difficulty Straightening the Knee Fully

Even without a true locking episode, many people with a meniscus tear find it difficult to fully straighten the knee. The joint may feel blocked or resistant at the end of its range, as though something is in the way.

This can affect everyday activities such as walking with a normal gait, standing for long periods, or sitting comfortably with the leg extended.

A Feeling of the Knee Giving Way

Some people describe a sensation that the knee is unstable or about to buckle, particularly when walking on uneven surfaces, descending stairs, or changing direction. This giving way sensation occurs because the damaged meniscus is no longer providing its normal stabilising function.

This symptom can also be associated with ligament injuries, which is one reason professional assessment is important for accurate diagnosis.

How Do Meniscus Tear Symptoms Compare to Other Knee Injuries?

Meniscus tear symptoms can overlap with several other common knee conditions, making self-diagnosis unreliable. A clinical examination remains the only reliable way to distinguish between them.

Condition Typical Onset Pain Location Swelling Pattern Mechanical Symptoms
Meniscus Tear Sudden (traumatic) or gradual (degenerative) Along the joint line (inner or outer) Gradual, over 24–48 hours Locking, catching, giving way
ACL Injury Sudden, often with a pop Diffuse, deep within the knee Rapid, significant within hours Instability, giving way
Patellofemoral Pain Gradual, activity-related Around or behind the kneecap Minimal or absent Grinding, crepitus
Knee Osteoarthritis Gradual, progressive Diffuse or along the joint line Variable, often after activity Stiffness, reduced range of motion

Joint line pain and giving way, for instance, appear in both meniscus tears and ACL injuries. Without a physical examination and imaging, it is not possible to determine the cause of your symptoms with confidence.

Can a Meniscus Tear Heal on Its Own?

Whether a meniscus tear can heal without treatment depends largely on where the tear is located within the cartilage. Some tears in the outer portion of the meniscus may heal with conservative management, while tears in the inner portion generally do not.

The key factor is blood supply. The outer edge of the meniscus receives a reasonable blood supply, which delivers the nutrients and cells needed for tissue repair. The inner portion has little to no blood supply, meaning the body has limited capacity to heal a tear in this region on its own.

Small tears in the blood-rich outer zone may settle with rest, physiotherapy, and time. Larger tears, tears in the inner zone, or tears that cause persistent mechanical symptoms such as locking are unlikely to resolve without intervention.

This is why the location of the tear, not just its size, plays a central role in determining the appropriate course of meniscus tear treatment.

The Blood Supply Factor

The meniscus is divided into zones based on blood supply:

  • Red zone (outer third): Well-vascularised; tears here have the greatest healing potential
  • Red-white zone (middle third): Partial blood supply; healing potential is variable
  • White zone (inner third): No blood supply; tears here do not heal naturally

Tear location is one of the most important factors a specialist considers when discussing treatment options with you.

What to Expect During Diagnosis

A diagnosis typically begins with a physical examination. Your doctor will ask about how and when the symptoms started, then assess your knee’s range of motion, stability, and areas of tenderness.

One commonly used test is the McMurray’s test, where the doctor gently rotates and bends the knee in a specific way to reproduce the catching or clicking sensation associated with a meniscus tear. It is a structured movement test designed to stress the meniscus in a controlled way. A positive result does not confirm the diagnosis on its own, but it provides useful clinical information.

An MRI (magnetic resonance imaging) scan is an essential and detailed tool for confirming the diagnosis. Unlike an X-ray, which shows bones, an MRI produces detailed images of cartilage, ligaments, and other soft tissues. It can reveal the size, location, and pattern of a tear, all of which inform treatment planning.

Understanding Meniscus Tear Treatment Options

Treatment for a meniscus tear is guided by the type, size, and location of the tear, as well as your age, activity level, and overall health. A conservative-first approach is appropriate for many patients, particularly those with smaller tears or degenerative changes.

Non-Surgical Approaches

Non-surgical management aims to reduce pain and inflammation, restore strength and mobility, and allow the body’s natural healing capacity to work where possible. Options may include:

  • Rest and activity modification: Avoiding movements that aggravate the knee while maintaining gentle activity
  • Physiotherapy: Targeted exercises to strengthen the muscles around the knee, particularly the quadriceps and hamstrings, to reduce the load on the joint
  • Medications: Anti-inflammatory medications to manage pain and swelling
  • Injections: Corticosteroid or hyaluronic acid injections may be considered in selected cases to relieve symptoms

Many patients with partial tears or degenerative tears experience meaningful improvement with these approaches over a period of weeks to months.

When Surgery May Be Considered

Surgery may be discussed when conservative treatment has not provided sufficient relief, when mechanical symptoms such as locking persist, or when the tear pattern is unlikely to heal without intervention.

Arthroscopic surgery, a minimally invasive procedure using a small camera and instruments inserted through tiny incisions, is the standard surgical approach. Depending on the tear, the surgeon may perform a repair (stitching the torn edges together) or a partial meniscectomy (removing the damaged portion). The choice between these options depends on the tear’s location, pattern, and the patient’s individual circumstances.

For a more detailed overview of surgical options, you may wish to explore the meniscus tear specialist page for further information.

Clinical Insights

A pattern that orthopaedic specialists frequently encounter is patients who delay seeking assessment because their symptoms seem manageable, or because they assume the knee will settle on its own with rest.

Dr Ong Kee Leong, a fellowship-trained senior consultant orthopaedic surgeon with subspecialty expertise in knee conditions and arthroscopic sports surgery, notes that early evaluation is particularly important for active individuals. When a tear is identified early, there is often a wider range of treatment options available, including approaches that aim to preserve as much of the native meniscus as possible. Delayed presentation, particularly when mechanical symptoms have been present for some time, can sometimes limit those options.

Dr Ong completed advanced fellowship training in sports surgery and arthroscopy in Hannover, Germany, and has been registered as a specialist in orthopaedic surgery with the Singapore Medical Council since 2011.

Taking the Right Steps After Noticing Symptoms

If you have been experiencing any of the symptoms described in this article, one practical step before a consultation is to document what you are noticing. Consider keeping a brief record of:

  • When the pain occurs (during activity, at rest, or both)
  • What movements or positions trigger or worsen it
  • Whether swelling comes and goes or is persistent
  • Any locking, catching, or giving way episodes, including how often they occur

This information gives your doctor a clearer picture of your symptom pattern and can help guide the examination and any imaging decisions.

When to Seek Professional Help

  • Swelling that persists beyond two weeks despite rest
  • Episodes of the knee locking or becoming stuck
  • Difficulty bearing weight on the affected leg
  • Symptoms that are worsening rather than improving with rest
  • Recurring giving way or instability during ordinary activities

Recurring discomfort that does not resolve fully may indicate that the underlying issue is not resolving on its own.

Commonly Asked Questions

How Long Do Meniscus Tear Symptoms Last Without Treatment?

This varies depending on the type and size of the tear. Small tears in the outer zone may gradually improve over several weeks with rest. However, tears in the inner zone, or those causing mechanical symptoms such as locking, are unlikely to resolve without treatment and may worsen over time. Persistent symptoms beyond a few weeks warrant professional evaluation.

Can I Still Exercise With a Suspected Meniscus Tear?

Low-impact activities such as swimming or cycling are generally better tolerated than high-impact or twisting movements. However, continuing to load a torn meniscus without guidance can worsen the tear. It is advisable to discuss your activity level with a specialist before resuming exercise, so that appropriate modifications can be recommended based on your specific situation.

Is a Meniscus Tear Visible on X-Ray?

No. X-rays show bone but do not visualise soft tissue structures such as cartilage. A meniscus tear cannot be seen on an X-ray. An MRI scan is the appropriate imaging investigation for assessing the meniscus and confirming the presence, size, and location of a tear.

What Happens If a Meniscus Tear Is Left Untreated?

An untreated tear, particularly one causing mechanical symptoms, can place abnormal stress on the surrounding cartilage and joint surfaces. Over time, this may contribute to accelerated cartilage wear and increase the risk of developing knee osteoarthritis. Timely assessment helps identify whether active treatment is needed to protect the joint in the longer term.

How Soon After Injury Should I See a Specialist?

If you experience significant swelling, inability to bear weight, or a locking sensation, it is reasonable to seek assessment within a few days. For milder symptoms, monitoring for one to two weeks is reasonable, but if there is no clear improvement, arranging a consultation is a sensible next step.

Next Steps

If the symptoms described in this article sound familiar, the practical next step is to arrange a clinical assessment. A physical examination combined with an MRI scan can confirm whether a meniscus tear is present and provide the information needed to discuss your options clearly.

Speak With a Knee Specialist About Your Symptoms

If you would like to learn more about meniscus tear symptoms and treatment options, a consultation with a knee specialist in Singapore can help you understand what is happening and what steps may be appropriate for your situation.

Book Appointment

Fill up the form and we will get back to you soon!

    Synergy Orthopaedic Group

    July 2026

    ACL vs Meniscus Tear: How to Tell the Difference

    If you have recently injured your knee, you may have heard the terms “ACL tear” and “meniscus tear” used almost interchangeably. They are not the same injury, though they can occur together, and the distinction matters when it comes to treatment.

    Both injuries can cause pain, swelling, and difficulty walking. Both can happen during sport or everyday activity. Yet they involve different structures, produce different symptoms, and often require different treatment approaches.

    What Is the ACL and What Does It Do?

    The anterior cruciate ligament (ACL) is one of the four main ligaments inside the knee joint. It runs diagonally through the centre of the knee, connecting the thigh bone (femur) to the shin bone (tibia). Its primary role is to control forward movement of the tibia and to stabilise the knee during rotational movements.

    When the ACL is intact, it keeps the joint controlled and predictable during movement. When it tears, the knee can feel loose, unreliable, or as though it might give way.

    ACL injuries are particularly common among active individuals who play sports that involve rapid changes of direction, jumping, or sudden stops. Sports such as football, basketball, badminton, and touch rugby are frequently associated with ACL tears. The injury often occurs without any direct contact.

    What Is the Meniscus and What Does It Do?

    The meniscus refers to two C-shaped pieces of cartilage that sit between the thigh bone and shin bone inside the knee joint. Each knee has two: the medial meniscus on the inner side and the lateral meniscus on the outer side. Together, they act as shock absorbers, distributing load evenly across the joint and protecting the surfaces of the bones.

    Beyond cushioning, the menisci also contribute to joint stability and help lubricate the knee. A tear in either meniscus disrupts this function, which can lead to pain, swelling, and mechanical symptoms such as clicking or locking.

    How Do ACL and Meniscus Injuries Happen?

    ACL Tear: Common Causes

    ACL tears most commonly result from sudden, high-energy movements rather than direct blows to the knee. Typical causes include:

    • Pivoting or cutting sharply while the foot remains planted on the ground
    • Landing awkwardly from a jump, particularly with the knee in a straightened or inward-collapsing position
    • Sudden deceleration, such as stopping abruptly while running
    • A direct collision that forces the knee into an unnatural position

    Many patients describe hearing or feeling a distinct “pop” at the moment of injury, followed by immediate swelling and a sense that the knee is unstable.

    Meniscus Tear: Common Causes

    Meniscus tears can occur in two broad ways: as an acute injury during activity, or as a gradual degenerative process over time.

    Acute meniscus tears often result from:

    • Twisting the knee while the foot is fixed to the ground
    • Deep squatting or kneeling under load
    • A direct impact to the knee during contact sports

    Degenerative meniscus tears develop gradually as the cartilage weakens with age and repeated stress. These tears can occur with relatively minor movements, such as rising from a low chair or stepping off a kerb.

    Can You Injure Both at the Same Time?

    Yes, and this is more common than many patients realise. ACL tears frequently occur alongside meniscus tears because the forces that rupture the ligament also stress the cartilage. When both structures are injured simultaneously, symptoms can overlap significantly, which is one reason why accurate diagnosis by a specialist is important.

    Feature ACL Tear Meniscus Tear
    Typical movement Pivoting, landing, sudden deceleration Twisting, deep squatting, gradual wear
    Sports commonly associated Football, basketball, badminton Football, running, racquet sports
    Acute or degenerative Typically acute Both acute and degenerative
    Contact required Often non-contact Can be non-contact or contact

    ACL vs Meniscus Tear Symptoms: What Does Each Feel Like?

    Symptoms can vary between individuals, and overlap between the two injuries makes self-diagnosis unreliable. Each injury does tend to produce a recognisable pattern of symptoms, however.

    Symptoms of an ACL Tear

    The hallmark features of an ACL tear include:

    • A loud or felt “pop” at the moment of injury
    • Rapid swelling that develops within a few hours of the injury
    • A feeling of instability or that the knee is “giving way,” particularly during weight-bearing or rotational movements
    • Difficulty continuing the activity that caused the injury
    • Pain, though the severity varies; some patients report surprisingly little pain initially despite significant ligament damage
    • Patients frequently describe the sensation that their knee cannot be trusted to hold them during movement.

    Symptoms of a Meniscus Tear

    Meniscus tear symptoms tend to be slightly different in character:

    • Pain located along the joint line (the inner or outer edge of the knee, depending on which meniscus is affected)
    • Swelling that may develop more gradually than with an ACL tear
    • A locking sensation, where the knee becomes temporarily stuck and cannot be fully straightened
    • Clicking, catching, or a sensation of something moving inside the knee
    • Stiffness, particularly after sitting for prolonged periods
    • Pain that worsens with twisting, squatting, or climbing stairs

    Overlapping Symptoms That Can Cause Confusion

    Symptom ACL Tear Meniscus Tear Both
    Swelling ✓ ✓ ✓
    Knee instability Primary feature Possible ✓
    Locking or catching Rare Primary feature Occasionally
    Popping sound at injury Common Less common Possible
    Joint-line tenderness Less specific Common ✓
    Difficulty bearing weight ✓ ✓ ✓
    Pain with twisting ✓ ✓ ✓

    How Are ACL and Meniscus Tears Diagnosed?

    Physical Examination

    Your specialist will begin with a thorough physical examination. For suspected ACL tears, the Lachman test is commonly used. The specialist applies gentle forward pressure to the shin bone while stabilising the thigh, assessing for excessive forward movement that would indicate ligament laxity.

    For suspected meniscus tears, the McMurray test is frequently performed. This involves rotating the lower leg while the knee is bent, listening and feeling for a click or pain response along the joint line.

    Other assessments may include observing your gait, checking range of motion, and evaluating for swelling or tenderness at specific points around the knee.

    MRI and Imaging

    An MRI (magnetic resonance imaging) scan is generally recommended to confirm the diagnosis and assess the extent of the injury. MRI produces detailed images of the soft tissues inside the knee, allowing the specialist to visualise the ligaments, cartilage, and other structures clearly.

    X-rays are also commonly taken to rule out bony injuries. Together, clinical examination and imaging give a comprehensive picture of what has happened inside the knee.

    How Does ACL vs Meniscus Tear Surgery Differ?

    Not every ACL or meniscus tear requires surgery. Treatment depends on the nature and severity of the injury, your age, activity level, and personal goals.

    ACL Reconstruction Surgery

    The ACL typically has limited capacity to heal on its own following a complete tear due to the environment and blood supply inside the joint. When surgical treatment is appropriate, the torn ligament is replaced with a graft, typically taken from a tendon in your own body (such as the hamstring or patellar tendon) or from a donor source. This procedure is known as ACL reconstruction surgery.

    The surgery is performed arthroscopically, meaning through small incisions using a camera and specialised instruments. This minimally invasive approach reduces tissue disruption and supports a more comfortable recovery.

    Meniscus Surgery: Repair vs Partial Removal

    Meniscus surgery falls into two main categories, and the choice between them depends largely on where the tear is located and what type of tear it is.

    • Meniscus repair: The torn edges of the meniscus are stitched back together. This approach is preferred when the tear is in the outer zone of the meniscus, where blood supply is adequate to support healing. Repair preserves as much of the natural cushion as possible.
    • Partial meniscectomy: The damaged portion of the meniscus is trimmed away, leaving the healthy tissue intact. This is more commonly performed for tears in the inner zone of the meniscus, where blood supply is limited and healing is unlikely.

    Non-Surgical Management: When Is It an Option?

    Non-surgical management may be appropriate in certain circumstances:

    • ACL tears: Patients who are less active, older, or willing to modify their activity level may manage well without reconstruction, particularly with targeted physiotherapy and bracing. However, continued instability can increase the risk of secondary damage to the meniscus and cartilage over time.
    • Meniscus tears: Small, stable tears, particularly degenerative tears in older patients, may respond well to physiotherapy, activity modification, and anti-inflammatory treatment.
    Feature ACL Tear Meniscus Tear
    Typical surgical approach Ligament reconstruction with graft Repair or partial removal (arthroscopic)
    Non-surgical option Possible in selected patients Often viable for small or degenerative tears
    General recovery timeline 6 to 9 months to return to sport 6 weeks to 4 months depending on procedure
    Influencing factors Activity level, instability, secondary damage Tear location, blood supply, patient age

    Why Tear Location Matters for Meniscus Treatment

    The meniscus has an outer zone with a good blood supply (often called the “red zone”) and an inner zone with limited blood supply (the “white zone”). Tears in the red zone are more likely to heal after repair. Tears in the white zone are less likely to heal and may require partial removal instead. Your specialist will assess the tear location to determine which approach is most appropriate for your injury.

    What Does Recovery Look Like for Each Injury?

    Recovery After ACL Reconstruction

    ACL reconstruction requires a longer and more structured rehabilitation process. Key milestones typically include:

    • First few weeks: Managing swelling, restoring range of motion, and beginning gentle strengthening exercises
    • Weeks 6 to 12: Progressive strengthening of the quadriceps, hamstrings, and hip muscles; improving balance and proprioception (the body’s sense of joint position)
    • Months 3 to 6: Sport-specific training, agility drills, and gradual return to higher-impact activities
    • 6 to 9 months: Return to competitive sport, subject to passing functional assessment criteria

    Physiotherapy plays an important role throughout this process. Rushing the return to sport before the graft has matured and strength has been fully restored increases the risk of re-injury.

    Recovery After Meniscus Surgery

    Recovery after meniscus surgery varies depending on whether a repair or partial removal was performed.

    • Partial meniscectomy: Recovery is generally faster, with many patients returning to daily activities within a few weeks and to sport within 6 to 8 weeks, depending on the extent of tissue removed.
    • Meniscus repair: Because the repair needs time to heal, recovery is longer, often comparable to ACL reconstruction in terms of the return-to-sport timeline. Weight-bearing may be restricted in the early weeks to protect the repair.

    In both cases, physiotherapy plays a central role in restoring strength, flexibility, and movement confidence.

    When to Seek Professional Help

    • A feeling that your knee is unstable or giving way during normal activity
    • Locking or catching sensations that prevent full straightening of the knee
    • Significant swelling that does not begin to settle within 48 to 72 hours
    • Inability to bear weight on the affected leg
    • Persistent pain that does not improve with rest

    In some cases, delayed assessment can allow secondary damage to develop, particularly if instability goes unaddressed.

    Commonly Asked Questions

    How do I know if I have torn my ACL or meniscus without an MRI?

    Without imaging, it is not possible to diagnose either injury with certainty. However, certain symptom patterns can suggest which structure may be involved. A loud pop at the time of injury followed by rapid swelling and a strong feeling of instability points more towards an ACL tear. Pain along the joint line, locking, or a catching sensation tends to be more associated with a meniscus tear. Symptoms overlap considerably, and many patients have both injuries simultaneously. A physical examination by a specialist, followed by an MRI if indicated, represents the standard clinical approach to confirm the diagnosis reliably.

    Can a torn meniscus heal on its own without surgery?

    Some meniscus tears can improve without surgery, particularly small, stable tears in the outer zone of the meniscus where blood supply is better. Degenerative tears in older, less active patients also often respond well to physiotherapy and activity modification. However, larger tears, tears that cause locking or persistent mechanical symptoms, and tears in areas with poor blood supply are less likely to resolve without intervention. Your specialist will assess the specific characteristics of your tear to advise on whether a non-surgical approach is appropriate.

    Is ACL reconstruction always necessary for a torn ACL?

    Not always. Whether ACL reconstruction is recommended depends on several factors, including the degree of instability, your activity level, your age, and whether other structures in the knee have also been injured. Some patients, particularly those who are less physically active or willing to modify their activities, manage well with physiotherapy and without surgical reconstruction. However, if instability persists or if you wish to return to sport involving pivoting and cutting movements, reconstruction is generally a more reliable long-term option.

    How long after ACL or meniscus surgery can I return to sports?

    After ACL reconstruction, many patients return to competitive sport between six and nine months post-surgery, provided they meet functional performance criteria. Returning too early before the graft has matured and strength has been fully restored increases the risk of re-injury. After a partial meniscectomy, return to sport may be possible within six to eight weeks. After a meniscus repair, the timeline is longer, often closer to four to six months, as the repaired tissue needs adequate time to heal. Your physiotherapist and specialist will guide you through a staged return-to-sport programme.

    Are ACL and meniscus injuries more common in certain sports?

    Both injuries are commonly seen in sports that involve rapid changes of direction, jumping, pivoting, and physical contact. Football, basketball, badminton, and rugby are frequently associated with ACL tears, largely because of the sudden deceleration and rotational forces involved. Meniscus tears are also common in these sports, as well as in activities that involve deep squatting or repetitive loading of the knee, such as weightlifting and running. Degenerative meniscus tears, however, can occur in individuals who are not particularly active, simply as a result of age-related changes in the cartilage.

    Speak with a Knee Specialist in Singapore

    If you are experiencing knee pain, instability, or mechanical symptoms after an injury, a consultation with an knee doctor in Singapore can provide the clarity you need. You may wish to explore your options for ACL and knee injury assessment in Singapore to better understand the treatment pathways available to you.

    Book Appointment

    Fill up the form and we will get back to you soon!

      Synergy Orthopaedic Group

      July 2026

      Hip replacement recovery spans six to twelve months in full, though many patients return to most daily activities well before that milestone. If you are considering or recovering from a hip replacement in Singapore, this guide walks you through the process from the first days post-surgery to full recovery and beyond.

      What Hip Replacement Recovery Involves

      Hip replacement recovery is the period during which your body heals after surgery, your implant integrates with surrounding bone, soft tissues repair, and you progressively regain strength, mobility, and function.

      Recovery unfolds in overlapping phases, each with its own goals and milestones.

      The First Few Days After Surgery

      In the immediate days following surgery, the clinical team’s priority is managing pain, preventing complications such as blood clots, and getting you moving safely. Most patients begin standing and taking short assisted steps within 24 hours of surgery. You will likely use a walking frame or crutches, and a physiotherapist will guide your first movements.

      Swelling, bruising, and fatigue are entirely normal at this stage.

      Weeks Two to Six: Early Rehabilitation

      Once you return home, structured physiotherapy begins in earnest. The focus during this phase is on restoring basic mobility, practising safe movement patterns, and preventing stiffness. You will follow hip precautions (movement restrictions that protect the new joint while tissues heal) and gradually increase the distance you walk each day.

      Many patients transition from a walking frame to a single crutch or walking stick during this period.

      Weeks Six to Twelve: Building Strength and Mobility

      By six weeks, most patients have a follow-up review with their orthopaedic surgeon. If healing is progressing well, activity restrictions are often eased. Physiotherapy shifts toward strengthening the muscles around the hip, improving balance, and refining your walking pattern.

      Climbing stairs with greater confidence and managing light household tasks independently are common milestones during this phase.

      Three to Six Months: Returning to Daily Activities

      Many patients return to work, resume social activities, and reintroduce low-impact exercise such as swimming or cycling. Residual stiffness and occasional discomfort may persist but typically continue to improve.

      Six to Twelve Months: Full Recovery and Beyond

      Full recovery, meaning the point at which the implant has integrated fully and surrounding muscles have regained their strength, generally occurs between six and twelve months. Some patients, particularly those who were very active before surgery, continue to notice gradual improvements beyond the twelve-month mark.

      Phase Typical Duration Key Milestones Common Activities Permitted
      Immediate post-operative Days 1 to 3 Standing, assisted walking Short walks with frame
      Early rehabilitation Weeks 2 to 6 Walking with aid, basic mobility Light household tasks, short walks
      Progressive strengthening Weeks 6 to 12 Reduced reliance on walking aid Stair climbing, light daily activities
      Return to daily life Months 3 to 6 Return to work (desk roles), low-impact exercise Swimming, cycling, driving (if cleared)
      Full recovery Months 6 to 12+ Full muscle strength, implant integration Most activities, including light recreational sport

      Factors That Affect Your Hip Replacement Recovery Timeline

      Several factors influence how quickly and smoothly you progress through each phase.

      Age and Overall Health

      Younger, healthier patients often recover more quickly, as their bodies tend to heal tissue and integrate implants more efficiently. However, age alone is not a barrier to a good outcome. Older adults who are otherwise well and medically optimised before surgery can achieve good results. Conditions such as diabetes, cardiovascular disease, or osteoporosis may require additional management to support healing.

      Pre-Surgery Fitness and Prehabilitation

      Prehabilitation refers to targeted exercise and conditioning undertaken in the weeks before surgery, with the goal of strengthening the muscles around the hip and improving cardiovascular fitness. Patients who engage in prehabilitation may find that their post-operative recovery progresses more smoothly. Entering surgery with stronger supporting muscles can give the new joint a better foundation to work from.

      If surgery is not imminent, maintaining as much physical activity as your hip allows is one of the most beneficial steps you can take.

      Type of Hip Replacement Performed

      Total hip replacement (where both the ball and socket of the joint are replaced) and partial hip replacement (hemiarthroplasty, where only one component is replaced) have somewhat different recovery trajectories. The surgical approach used, whether the surgeon accesses the joint from the front (anterior), side (lateral), or back (posterior), also influences early recovery, particularly in terms of hip precautions and the risk of dislocation.

      Your orthopaedic surgeon will discuss which approach is most appropriate for your anatomy and condition.

      Commitment to Physiotherapy and Rehabilitation

      Adherence to your physiotherapy programme is one of the most significant factors within your control. Patients who attend sessions consistently, complete home exercise programmes, and follow their physiotherapist’s guidance tend to achieve better functional outcomes and reach milestones sooner. Skipping sessions or pushing too hard too soon can both delay progress.

      What Does Physiotherapy After Hip Replacement Look Like?

      Physiotherapy after hip replacement follows a structured, progressive plan that begins in hospital and continues for several months after you return home.

      Early Mobility Exercises

      In the first weeks, physiotherapy focuses on gentle range-of-motion exercises, ankle pumps (to encourage circulation and reduce clot risk), and practising movements such as getting in and out of bed, sitting down, and climbing steps safely.

      Your physiotherapist will also teach you the specific hip precautions relevant to your surgical approach, so you move confidently without placing undue stress on the healing joint.

      Progressive Strengthening and Balance Work

      As healing progresses, exercises become more challenging. Resistance work targeting the hip abductors (the muscles on the outer hip), quadriceps, and glutes helps stabilise the joint and restore your natural walking pattern. Balance and proprioception (your body’s sense of joint position) training is introduced to reduce the risk of falls and improve confidence on uneven ground.

      Gait retraining, which involves practising how you walk to eliminate compensatory patterns that may have developed during years of hip pain, is an important component of this phase.

      Prehabilitation Can Give You a Head Start

      Starting targeted hip and leg strengthening exercises before surgery may help support your post-operative recovery. Even a few weeks of consistent prehabilitation can help you enter surgery with stronger muscles, better cardiovascular conditioning, and a clearer understanding of the exercises you will be doing afterwards. If your surgery date is confirmed, ask your physiotherapist about a prehabilitation programme.

      Common Concerns During Hip Replacement Recovery

      Managing Pain and Swelling

      Some degree of pain and swelling is expected in the weeks following surgery. Your surgical team will prescribe a pain management plan that may include oral analgesics, anti-inflammatory medication, and ice therapy. Pain typically decreases progressively over the first six weeks, though you may notice it fluctuates with activity levels.

      Swelling can persist for several months, particularly towards the end of the day or after increased activity. Elevating the leg when resting and applying ice packs (wrapped in a cloth to protect the skin) can help manage this.

      Sleep and Comfort Adjustments

      Many patients find sleep challenging in the early weeks. Discomfort, unfamiliar positioning requirements (such as sleeping with a pillow between the legs to maintain hip alignment), and post-operative fatigue can all disrupt rest. Using a firm mattress and arranging pillows strategically can help. Most patients find sleep quality improves noticeably by weeks four to six.

      If pain is consistently preventing sleep, discuss this with your doctor, as adjustments to your pain management plan may be helpful.

      Emotional Wellbeing and Patience with Progress

      Reduced independence during recovery can be emotionally challenging, particularly for people who are accustomed to being active or self-sufficient. Feelings of frustration, low mood, or impatience with the pace of progress are common and valid. Recovery is rarely linear; some days will feel like a step backwards, and that is a normal part of the process.

      Staying connected with family and friends, maintaining small daily routines, and celebrating incremental milestones can all support your emotional wellbeing during this period.

      When Can You Return to Work and Activities After Hip Replacement?

      Most patients can return to desk-based work within four to six weeks of surgery, provided they are comfortable sitting for extended periods and can manage the commute safely. For physically demanding roles involving prolonged standing, heavy lifting, or uneven terrain, a return to work timeline of three to six months is more realistic, and a phased return is often advisable.

      Driving is typically permitted once you have sufficient strength and reaction time to operate the vehicle safely, and once you are no longer taking strong opioid pain medication. For most patients, this falls between six and twelve weeks after surgery, though your surgeon will advise based on your individual progress.

      Activity Typical Timeframe Considerations
      Desk work 4 to 6 weeks Ensure comfortable seating and ability to take regular movement breaks.
      Driving 6 to 12 weeks Surgeon clearance required; no strong opioid medication.
      Light household tasks 2 to 6 weeks Avoid bending beyond hip precaution limits.
      Swimming 3 to 4 months Once the wound is fully healed and the surgeon has cleared the activity.
      Cycling (stationary) 6 to 8 weeks Low-impact option suitable for early rehabilitation.
      Cycling (outdoor) 3 to 6 months Balance and terrain considerations apply.
      Golf 4 to 6 months Rotational forces on the hip require adequate healing.
      Hiking 6 to 12 months Uneven terrain demands full strength and stability.
      Air travel (long-haul) 6 to 12 weeks minimum Blood clot risk; discuss timing and precautions with your surgeon.

      Clinical Insights

      Patients who enter surgery with realistic expectations and a clear understanding of the recovery process tend to cope better with the challenges of rehabilitation. Recovery from hip replacement surgery in Singapore is not simply about the surgery itself; it is about the weeks and months of structured work that follow.
      The type of implant, the surgical approach, the patient’s anatomy, and their pre-operative condition all inform what a realistic and achievable recovery looks like for each individual. Structured physiotherapy, consistent follow-up, and open communication between patient and surgeon are the cornerstones of a well-managed recovery.

      Setting Yourself Up for a Smoother Recovery

      Preparation before surgery can make a meaningful difference to how smoothly your recovery unfolds. Consider the following steps:

      • Prepare your home environment: Remove trip hazards such as loose rugs, install grab rails in the bathroom, and arrange a sleeping area on the ground floor if your bedroom requires significant stair climbing.
      • Arrange practical support: Plan for help with meals, transport, and household tasks for at least the first two to four weeks.
      • Start prehabilitation: If time allows, begin gentle hip and leg strengthening exercises before surgery.
      • Follow post-operative instructions carefully: Hip precautions, wound care, and medication schedules are all important components of early recovery.
      • Stay consistent with physiotherapy: Attend all scheduled sessions and complete your home exercise programme as directed.

      When to Seek Professional Help During Recovery

      • Signs of infection: Fever above 38°C, increasing redness or warmth around the wound, unusual or foul-smelling discharge from the surgical site.
      • Sudden increase in pain: A significant and unexplained worsening of pain, particularly if it follows a fall or unusual movement.
      • Leg swelling with calf pain: This combination can indicate a deep vein thrombosis (a blood clot in the leg), which requires urgent assessment.
      • Feeling of instability or a “clunking” sensation: A sense that the hip joint is unstable, or a clicking or clunking feeling that is new or worsening, should be evaluated.
      • Shortness of breath or chest pain: These symptoms can indicate a pulmonary embolism (a blood clot in the lungs) and require emergency medical attention.

      When in doubt, contact your surgeon’s team.

      Commonly Asked Questions

      How painful is recovery after hip replacement?

      Pain is expected in the first few weeks and is typically managed with prescribed medication. Most patients find that pain decreases noticeably by weeks four to six. Discomfort during exercise is normal, but sharp or worsening pain at rest should be discussed with your surgeon. Many patients report that post-operative pain, while present, is more manageable than the chronic pain they experienced before surgery.

      How long will I need to use a walking aid?

      Most patients use a walking frame initially, then transition to a single crutch or walking stick by weeks two to four. Many are able to walk unaided by six to eight weeks, though this varies depending on individual progress and surgical approach. Your physiotherapist will advise when it is safe to reduce reliance on the aid.

      Can hip replacement surgery fail, and what are the signs?

      Hip replacement complications are uncommon but possible. Signs that may indicate a problem include persistent or worsening pain beyond the expected recovery period, instability or dislocation of the joint, swelling that does not resolve, or signs of infection. Implant loosening can occur over many years. Regular follow-up appointments with your orthopaedic surgeon allow for early detection of any issues.

      Is hip replacement recovery different for older adults?

      Recovery timelines may be somewhat longer for older adults, particularly those with other health conditions or reduced baseline fitness. However, age alone does not determine outcome. Older patients who are medically well-prepared and commit to rehabilitation can achieve good functional results. Your surgical and rehabilitation team will tailor the recovery plan to your specific needs and circumstances.

      How long does a hip replacement implant last?

      Modern hip replacement implants are designed to be durable. Many patients may find that an implant functions well for fifteen to twenty years or more, though this depends on factors such as activity level, body weight, and implant type. Your orthopaedic surgeon will discuss implant options and longevity expectations during your pre-operative consultation.

      Speak with an Orthopaedic Specialist About Your Hip Replacement Recovery

      Every patient’s hip replacement recovery in Singapore is unique, and the most reliable guidance comes from a specialist who can assess your specific condition, surgical history, and rehabilitation needs. If you are considering hip replacement or would like to understand more about hip replacement in Singapore, a consultation with a hip specialist in Singapore is a practical next step toward making an informed decision.

      Book Appointment

      Fill up the form and we will get back to you soon!

        Synergy Orthopaedic Group

        July 2026

        Whether you run along the park connector network, play recreational badminton, or train at the gym several times a week, sports injuries are a common experience for active people in Singapore.

        Sports Injuries in Singapore

        Singapore’s year-round warm weather and growing fitness culture mean that more people than ever are running, cycling, swimming, and playing team sports. An active lifestyle brings a real, if manageable, risk of injury.

        Many people push through discomfort because they love their sport, do not want to lose fitness, or simply are not sure whether what they are feeling is serious. Knowing the difference between normal post-exercise soreness and a genuine injury, and understanding when to get it assessed, puts you in a stronger position to recover well.

        What Counts as a Sports Injury?

        A sports injury is any physical damage to muscles, tendons, ligaments, bones, or joints that occurs as a result of physical activity, whether during sport, exercise, or recreational movement. Sports injuries can happen suddenly or develop gradually over time, and they affect people of all fitness levels, not just competitive athletes.

        Weekend warriors who play social basketball on Saturday mornings, gym-goers who increase their weights too quickly, and retirees who take up swimming for the first time may all be susceptible. What matters is not the level of sport but the demands placed on the body relative to its current capacity.

        Acute Injuries

        Acute injuries happen suddenly, usually as the result of a single traumatic event. A fall, a collision, a sudden change of direction, or an awkward landing can all cause an acute injury. You typically feel pain immediately, and symptoms such as swelling, bruising, or an inability to move the affected area may develop within minutes to hours. Examples include a twisted ankle, a torn knee ligament, or a dislocated shoulder.

        Overuse Injuries

        Overuse injuries develop gradually over weeks or months. They occur when repetitive stress is applied to a body part without enough time for recovery in between. Think of it like bending a paper clip back and forth repeatedly: each individual bend seems harmless, but the cumulative effect causes it to weaken and eventually snap. Common overuse injuries include tennis elbow, shin splints, and rotator cuff tendinopathy. Pain often starts as a mild ache that worsens with activity and may eventually become present even at rest.

        Common Causes of Sports Injuries

        Most injuries are not simply bad luck. They tend to result from identifiable, addressable factors.

        Inadequate Warm-Up and Conditioning

        Jumping straight into intense activity without preparing your body is one of the most common contributors to injury. A proper warm-up gradually increases blood flow to muscles, improves joint mobility, and primes your neuromuscular system (the communication network between your brain and muscles) for the demands ahead. This is particularly relevant for people playing sports in Singapore’s heat, where the temptation to skip a warm-up is sometimes greater because the ambient temperature already feels warm.

        Overtraining and Insufficient Rest

        When you train, you create small amounts of stress in your muscles and connective tissues. Rest periods allow those tissues to repair and grow stronger. Without adequate recovery, the cumulative damage outpaces the body’s ability to heal, increasing the risk of both overuse injuries and stress fractures. This pattern is common among motivated recreational athletes who train intensively during the week on top of demanding work schedules.

        Poor Technique or Equipment

        Incorrect movement patterns place abnormal loads on joints and soft tissues. A runner who overpronates (rolls their foot inward excessively with each step) places added stress on the knee and hip. A swimmer with poor shoulder mechanics may develop rotator cuff irritation over time. Ill-fitting footwear, worn-out trainers, or rackets strung at the wrong tension can compound the problem. Small technical errors, repeated thousands of times, accumulate into injury.

        Environmental and Surface Factors

        Singapore’s hard court surfaces, common in public sports facilities, transmit more impact force through the legs compared with softer surfaces such as grass or rubberised tracks. Playing in high heat and humidity also increases fatigue more quickly, which can compromise technique and coordination in the later stages of a game or training session. Fatigue is a well-recognised contributor to injury risk.

        Common Causes of Sports Injuries

        Cause Example Activities Body Parts Most Often Affected
        Inadequate warm-up Badminton, football, running Hamstrings, calves, Achilles tendon
        Overtraining / insufficient rest Distance running, cycling, swimming Shins, knees, shoulders
        Poor technique Tennis, golf, weightlifting Elbow, lower back, rotator cuff
        Ill-fitting or worn equipment Running, court sports Feet, ankles, knees
        Hard or uneven surfaces Basketball, netball, running Ankles, knees, hips
        Heat and fatigue All outdoor sports Generalised; coordination-related injuries

        Which Sports Injuries Are Most Common?

        Certain injuries appear repeatedly in orthopaedic practice, and they tend to cluster around specific body regions.

        Shoulder Injuries

        The shoulder is the most mobile joint in the body, which also makes it one of the most vulnerable. Common shoulder injuries in active individuals include:

        • Rotator cuff tears or tendinopathy: The rotator cuff is a group of four muscles and their tendons that stabilise the shoulder. Repetitive overhead movements in swimming, throwing sports, or racket sports can cause gradual wear or acute tearing. Symptoms include pain at the front or side of the shoulder, weakness when lifting the arm, and discomfort at night.
        • Shoulder impingement syndrome: Tendons become pinched between the bones of the shoulder during arm elevation, causing pain and restricted movement.
        • Shoulder dislocation: Common in contact sports and falls, where the upper arm bone slips out of the shoulder socket. Recurrent instability after an initial dislocation is a frequent reason patients seek specialist assessment.

        Knee Injuries

        The knee absorbs significant force during running, jumping, and pivoting, making it one of the most commonly injured joints in sport.

        • Anterior cruciate ligament (ACL) tears: The ACL is a stabilising ligament inside the knee. It is commonly injured during sudden stops, pivots, or landing from a jump. Many people describe hearing or feeling a “pop,” followed by rapid swelling and a sense of instability.
        • Meniscus tears: The menisci are two C-shaped cartilage pads that cushion and stabilise the knee. Tears can occur acutely or through cumulative wear. Symptoms include pain along the joint line, swelling, and sometimes a locking or catching sensation.
        • Patellofemoral pain syndrome: Often called “runner’s knee,” this presents as aching pain around or behind the kneecap, typically worsening with prolonged sitting, stair climbing, or running.

        Foot and Ankle Injuries

        • Ankle sprains: One of the most common acute sports injuries, typically involving the ligaments on the outer side of the ankle after an inward roll. Symptoms include immediate pain, swelling, and bruising.
        • Achilles tendon injuries: Ranging from tendinopathy (gradual onset pain and stiffness at the back of the heel) to acute rupture (a sudden, sharp pain often described as feeling like a kick or a snap).
        • Plantar fasciitis: Pain at the base of the heel, often worst with the first steps in the morning, caused by irritation of the thick band of tissue along the sole of the foot.

        Hand, Wrist, and Elbow Injuries

        • Tennis elbow (lateral epicondylitis): Pain and tenderness on the outer side of the elbow, caused by overloading the tendons that attach there. Despite its name, it occurs in many activities beyond tennis, including badminton, golf, and even repetitive work tasks.
        • Golfer’s elbow (medial epicondylitis): Similar to tennis elbow but affecting the inner side of the elbow.
        • Wrist sprains and fractures: Common in falls where the hand is outstretched to break the impact.
        • Finger ligament injuries: Frequent in ball sports, where a finger is bent forcefully in the wrong direction.

        Common Sports Injuries by Body Region

        Body Region Injury Typical Cause Key Symptoms
        Shoulder Rotator cuff tear Overhead repetitive activity or acute strain Shoulder pain, weakness, night pain
        Shoulder Dislocation Fall or contact sport impact Visible deformity, severe pain, inability to move arm
        Knee ACL tear Pivoting, landing, sudden stop “Pop,” rapid swelling, instability
        Knee Meniscus tear Twisting on a bent knee Joint line pain, swelling, locking sensation
        Foot and ankle Ankle sprain Inward roll of the foot Outer ankle pain, swelling, bruising
        Foot and ankle Achilles tendon rupture Sudden push-off or acceleration Sharp pain at back of heel, inability to push off
        Elbow Tennis elbow Repetitive gripping or wrist extension Outer elbow pain, weak grip
        Wrist Sprain or fracture Fall on outstretched hand Pain, swelling, reduced movement

        How Do You Know If a Sports Injury Is Serious?

        General muscle soreness that appears one to two days after activity and gradually improves is a normal part of training. A sports injury, by contrast, tends to produce pain that is more localised, more persistent, or associated with other changes in how the affected area functions.

        The following features suggest you may be dealing with something that warrants assessment rather than rest alone:

        • Pain that is sharp, severe, or immediately disabling
        • Swelling that develops rapidly or does not settle within a few days
        • Bruising that spreads beyond the immediate area of impact
        • A feeling that a joint is unstable, giving way, or no longer feels “right”
        • Locking or catching sensations in a joint
        • Inability to bear weight through a limb or to move a joint through its normal range
        • Numbness, tingling, or weakness in a limb

        Mild soreness that improves with rest, responds to ice and gentle movement, and does not limit your daily activities is generally less concerning. If you are unsure, it is always reasonable to have a professional assessment.

        Red Flags That Warrant Prompt Medical Attention

        Seek prompt medical attention if you experience any of the following:

        • Visible deformity of a joint or limb
        • Severe swelling that develops within minutes of injury
        • Complete inability to move or bear weight on an injured limb
        • A “pop” or “snap” heard or felt at the time of injury, followed by significant swelling
        • Numbness or loss of sensation in the affected area
        • Symptoms that worsen despite rest over several days

        What Happens If You Ignore a Sports Injury?

        Continuing to load an injured structure can worsen the initial damage. A partial ligament tear that might have healed with appropriate early management can progress to a complete rupture. A stress reaction in bone, if not offloaded in time, may develop into a full stress fracture.

        Over time, untreated injuries can lead to chronic instability, persistent pain, and compensatory movement patterns that place abnormal stress on surrounding joints. An ankle that never fully rehabilitates after a sprain is more likely to be re-sprained and may develop long-term joint stiffness or instability. Knee injuries left unmanaged can accelerate cartilage wear.

        Early assessment tends to open up a wider range of treatment options, many of which are simpler and less invasive than those required once a problem has become established.

        How Are Sports Injuries Diagnosed and Treated?

        When you see an orthopaedic specialist for a sports injury, the assessment typically begins with a detailed clinical history and physical examination. Your doctor will ask about how the injury occurred, your symptoms, your activity level, and any previous injuries to the same area. This information, combined with a hands-on examination of the affected joint or structure, often provides a clear working diagnosis.

        Imaging may be requested to confirm the diagnosis or assess the extent of injury:

        • X-rays are useful for identifying fractures and assessing bone alignment.
        • Ultrasound can visualise soft tissue structures such as tendons and ligaments in real time.
        • MRI (magnetic resonance imaging) provides detailed images of soft tissues including ligaments, cartilage, and muscles, and is particularly helpful for complex joint injuries.

        Conservative and Non-Surgical Approaches

        Many sports injuries respond well to non-surgical management. Treatment is tailored to the nature and severity of the injury, but common approaches include:

        • Rest and activity modification: Reducing or temporarily stopping the activity that caused the injury to allow healing to begin.
        • Physiotherapy: Guided exercises to restore strength, flexibility, and movement control. Physiotherapy is often a central part of recovery for both acute and overuse injuries.
        • Ice, compression, and elevation: Useful in the early stages to manage swelling and pain.
        • Medications: Anti-inflammatory medications may be recommended to manage pain and swelling in the short term.
        • Bracing or orthotics: Supportive devices to protect an injured structure or correct biomechanical factors contributing to the injury.
        • Injections: In selected cases, corticosteroid or other injections may be used to reduce inflammation and facilitate rehabilitation.

        When Surgery May Be Considered

        Surgery is considered when conservative measures have not provided sufficient improvement, when the structural damage is severe enough that non-surgical management is unlikely to restore adequate function, or when the patient’s activity goals require a level of joint stability that cannot be achieved without surgical repair.

        Common procedures include arthroscopic surgery (keyhole surgery performed through small incisions using a camera and fine instruments) for conditions such as ACL reconstruction, meniscus repair, and shoulder stabilisation. Arthroscopic approaches are associated with smaller incisions, less disruption to surrounding tissue, and, in many cases, a smoother recovery compared with open surgical techniques.

        Taking an Active Role in Your Recovery

        Recovery from a sports injury requires active participation. Following your rehabilitation programme consistently, even when progress feels slow, is an essential step in supporting your recovery. Physiotherapy exercises prescribed between sessions are not optional extras; they are a core part of the treatment.

        Communicating openly with your specialist and physiotherapist matters too. If something is not improving as expected, or if you experience new symptoms, raising this early allows your care team to adjust the plan. Setting realistic return-to-activity milestones, rather than rushing back to sport, can help reduce the risk of re-injury.

        When to Seek Professional Help

        • Your symptoms have not improved after two to four weeks of conservative management
        • You experienced a significant acute injury such as a suspected ligament tear, dislocation, or fracture
        • You have joint instability, locking, or persistent swelling
        • You have had recurrent injuries to the same area
        • You are an active individual who needs a clear diagnosis and structured plan to return to sport safely

        For minor strains and sprains that improve steadily with rest, ice, and gentle movement within the first few days, a visit to your GP is a reasonable first step. Your GP can assess the injury, provide initial management advice, and refer you onward if needed.

        An orthopaedic specialist can provide a detailed structural assessment, arrange appropriate imaging, and work with you on a treatment plan that matches both your injury and your activity goals.

        Commonly Asked Questions

        Can I Continue Exercising With a Minor Sports Injury?

        This depends on the nature and location of the injury. For minor muscle soreness or a mild strain, low-impact activity that does not aggravate the affected area may be appropriate. However, continuing to train through pain that worsens with activity, or that involves a joint, is generally not advisable. If you are unsure, a professional assessment will give you a clearer picture of what is safe.

        How Long Does Recovery From a Sports Injury Usually Take?

        Recovery timelines vary considerably depending on the type and severity of the injury, your age, your overall health, and how consistently you engage with rehabilitation. Minor soft tissue injuries may resolve within a few weeks. More significant injuries, such as ligament tears requiring surgery, may involve a structured rehabilitation period of several months. Your specialist will provide a realistic timeline based on your specific situation.

        Do I Need an MRI for Every Sports Injury?

        No. Many sports injuries can be accurately diagnosed through clinical examination alone, or with the addition of an X-ray. MRI is most useful for complex joint injuries, suspected ligament or cartilage damage, or when the diagnosis remains unclear after initial assessment. Your doctor will recommend imaging based on what is clinically indicated for your injury.

        Can Sports Injuries Be Prevented?

        Many sports injuries can be reduced in frequency and severity with sensible precautions. These include warming up adequately before activity, building training load gradually, using appropriate equipment and footwear, learning correct technique, and allowing sufficient recovery time between sessions. No approach eliminates injury risk entirely, but these measures may help reduce the likelihood of injury.

        Is Surgery Always Necessary for Ligament Tears?

        No. Not all ligament tears require surgery. Many partial tears, and even some complete tears in less mechanically demanding individuals, can be managed successfully with physiotherapy and activity modification. Surgery is considered when conservative management does not restore adequate function, or when the patient’s activity level requires a degree of joint stability that rehabilitation alone cannot achieve. Your orthopaedic specialist will discuss the most appropriate approach for your specific injury and goals.

        Next Steps

        If you have recognised any of the symptoms or patterns described in this article, use the red flags outlined earlier as a practical guide. If your symptoms are mild and improving, continue to monitor them and support your recovery with rest and appropriate movement. If they are persistent, worsening, or associated with instability or significant functional limitation, arrange a professional assessment sooner rather than later.

        Speak With an Orthopaedic Sports Injury Specialist

        If you are experiencing persistent or significant sports injury symptoms, a  sports injury specialist assessment can help clarify your diagnosis and outline your options. Learn more about orthopaedic sports injury assessment and treatment to understand how a personalised, structured approach to your recovery may support your return to the activities that matter to you.

        Book Appointment

        Fill up the form and we will get back to you soon!

          Synergy Orthopaedic Group

          July 2026

          Many of us in Singapore are “weekend athletes”—spending our weekdays chained to an office desk, only to dive headfirst into intense sports and gym sessions over the weekend. While staying active is wonderful, this sudden “sedentary to high-intensity” pattern often places unexpected stress on your body, which may lead to stubborn joint strains or sports injuries that often seem difficult to resolve.

          Watch this video from this interview with 8world and what an orthopaedic surgeon in Singapore typically recommends to help support safe training and prevention for common injuries:

          Why Desk Workers Are More Prone to Injuries During Weekend Exercise

          The “sedentary workweek combined with intense weekend exercise” is a common contributing factor to sports injuries for many office workers in Singapore.

          This risk is particularly high for individuals aged 40 to 60s. As Dr Ong Kee Leong highlighted in his 8world interview, many adults in this age group begin exercising—such as running or gym training—to combat sarcopenia (age-related muscle loss).

          According to Dr Ong, injuries frequently occur due to several key factors:

          • Sudden Spikes After Prolonged Inactivity: Shifting abruptly from a sedentary state to intense weekend sports places extreme, unexpected stress on your joints.
          • Lack of Gradual Progression: Many individuals jump straight into high-frequency or high-intensity workouts before their bodies are ready.
          • Relying on Casual Guidance: Many beginners rely on casual advice from friends or unverified online fitness videos, which may not suit their current body condition.
          • Overestimating Fitness Levels & Poor Preparation: Exercising without proper warm-ups or attempting workouts that exceed one’s actual physical capacity.

          Common Sports Injuries Seen in Active Adults

          When you abruptly switch from an office chair to high-impact activities, certain parts of your body bear the brunt of the sudden stress. Here are the most common sports injuries and symptoms that orthopaedic surgeons frequently treat among Singapore’s active adults:

          Knee Pain After Running or High-Impact Exercise

          Knee pain is one of the most common complaints among runners and gym-goers. Some people notice discomfort around the kneecap after running, while others experience pain during squats, stair climbing, or jumping exercises.

          These symptoms may develop when training intensity increases too quickly or when the joints are placed under repeated stress without adequate recovery.

          Shoulder Strain After Gym Training

          Shoulder pain may occur after weight training, racket sports, or repetitive overhead movements. Poor exercise form, overtraining, or returning to intense workouts too quickly after a sedentary week may place additional stress on the shoulder joint.

          Some people notice discomfort when lifting the arm, carrying weight, or performing upper body exercises.

          Ankle Sprains During Football or Court Sports

          Sports involving sudden direction changes such as football, badminton, or basketball may increase the risk of ankle sprains and ligament injuries.

          While some ankle injuries recover with rest and rehabilitation, recurring sprains or persistent instability may sometimes require further assessment.

          Is It Just Muscle Soreness — Or Something More?

          It is entirely normal to feel a bit stiff after a strenuous weekend workout. However, many active adults mistake a genuine sports injury for “normal post-workout soreness” and continue to train through the discomfort, which could potentially worsen the condition.

          To help you identify whether your pain requires professional medical attention, here is a quick look at how typical muscle soreness compares to a potential sports injury:

          Feature Typical Post-Workout Soreness (DOMS) Possible Sports Injury
          Onset & Duration Develops 24–48 hours after exercise; typically improves within a few days. May occur suddenly during exercise or persists/worsens weeks later.
          Pain Type Dull, generalized muscle ache or tightness. Sharp, stabbing, or highly localized pain in a specific joint or tendon.
          Swelling & Mobility Typically no visible swelling; temporary stiffness that improves once you warm up. Visible swelling, bruising, joint stiffness, or a feeling of joint instability.
          Impact on Movement Mild discomfort that doesn’t stop you from performing daily activities. Severe pain that makes walking, bearing weight, or moving the affected joint difficult.

          When Should You Seek An Orthopaedic’s Advice?

          It is advisable to seek a professional orthopaedic evaluation as soon as possible if you experience any of the following symptoms:

          • Acute, intense pain during or after exercise that does not typically improve with rest.
          • Puffiness or lock-up around a joint (such as the knee, ankle, or shoulder) that restricts your normal movement.
          • Pain or discomfort that shows minimal to no improvement even after days of complete rest and over-the-counter anti-inflammatory medications.
          • Chronic discomfort or a dull ache that lingers for several weeks.
          • Numbness or Tingling. “Pins and needles” sensations radiating down from your lower back into your legs, or from your neck into your arms, which may indicate issues related to the spine.

          How Orthopaedic Surgeons Diagnose Sports Injuries

          A clinical diagnosis begins with a detailed discussion about your medical history, recent workout patterns, and daily workplace habits to understand the mechanics of your injury.

          During a consultation, an orthopaedic specialist will typically perform:

          • Symptom Location Review: Pinpointing the exact source of your pain, whether it originates in a joint, tendon, or muscle.
          • Movement & Flexibility Assessments: Testing your range of motion and checking for muscle tightness, joint instability, or signs of nerve irritation.
          • Physical Examination: Gently pressing on the affected areas to check for swelling, tenderness, and structural alignment.

          If your symptoms are complex, an advanced imaging like X-rays or MRI scans may be recommended to help guide a treatment plan.

          Treatment Options for Sports Injuries

          Many cases may improve with conservative treatment, especially when addressed early. Depending on your assessment, management may include:

          • Temporary restriction of aggravating activities to give injured tissues time to heal.
          • Physiotherapy and stretching exercises to improve overall stability.
          • Short-term use of prescribed anti-inflammatory medication to manage acute pain and swelling.
          • Improving posture and daily workstation setup to reduce chronic muscle strain.

          If symptoms do not improve with basic rest, guided injections or more targeted specialist rehabilitation programmes may sometimes be considered to help facilitate recovery.

          Injury Prevention Tips for Active Adults in Singapore

          To help you train safely, here are key injury prevention tips recommended by Dr Ong Kee Leong:

          Avoid weekend-only intense workouts

          Do not pack all your exercise into the weekend. A consistent weekly routine allows your muscles and joints to adapt gradually and may help reduce the risk of overuse injuries.

          Always warm up before exercise
          Spend 10–15 minutes on light cardio and dynamic stretches to prepare your muscles and help reduce strain risk.

          Train according to your body, not others
          Adjust intensity based on your fitness level, age, and recovery ability. Pain during movement is a signal to scale back.

          Reduce long sitting time
          If you work at a desk, stand or move every 45-60 minutes to help prevent stiffness and support joint health.

          For individuals with recurring pain or concerns about safe exercise, consulting an orthopaedic surgeon in Singapore can help provide tailored guidance based on your condition.

          Frequently Asked Questions

          Can I just walk off a gym injury, or should I actually go see a doctor?

          If you experience sharp or highly localized pain, visible swelling, or any tingling sensations down your limbs, these could be signs of a more significant sports injury. In such cases, having it evaluated by a doctor is often a practical next step.

          What doctor should I see for a sports injury, and who can diagnose it?

          For general joint strains or exercise-related pains, you can typically start by consulting a general practitioner (GP)for an initial assessment. If the injury involves persistent pain that doesn’t resolve with rest, an orthopaedic surgeon is usually the one to provide a clinical diagnosis and guide a tailored recovery plan.

          Is there any safe way to heal a sports injury faster?

          One of the ways to support safe recovery is to address the pain early instead of training through it. Steps like temporary rest, guided physiotherapy, and managing swelling may help facilitate your body’s natural healing process.

          Conclusion

          Balancing a busy workweek with weekend sports is excellent for long-term health, but it requires listening to your body. Minor aches left ignored may gradually alter your movement patterns, potentially leading to more complex joint issues later on.

          To help facilitate a safe recovery and obtain a clinical diagnosis for persistent joint pain or sports injuries that do not resolve with rest, it is best to consult a professional orthopaedic surgeon who can develop a tailored plan to help you return to the sports you enjoy.

          Book Appointment

          Fill up the form and we will get back to you soon!

            Synergy Orthopaedic Group

            back to top